Why Hives Appear After a Hospital Stay and How to Treat Them
Understanding the Trigger: Common Causes
Coming home with a rash that flashes red, raised welts can be unsettling, especially after a recent admission. Those itchy plaques—medically called urticaria—often have a clear link to something that happened while you were under care. Below we untangle the most frequent culprits that turn a hospital stay into a hive‑making event.
Medications and IV fluids
- Antibiotics: Penicillins, sulfonamides and certain cephalosporins are notorious for provoking allergic skin reactions.
- Contrast agents: Used for CT or MRI scans, the iodine‑based dyes can trigger a rapid histamine release in sensitive patients.
- Intravenous fluids: Even saline or dextrose solutions may contain additives (like preservatives) that act as hidden allergens.
- Analgesics and sedatives: Opioids, NSAIDs and benzodiazepines sometimes cause non‑IgE mediated hives, especially when combined with other drugs.
Environmental allergens in the hospital
Hospitals are not sterile bubbles. Latex gloves, cleaning agents, and even certain bedding fabrics can release proteins that some people recognize as threats. If you have a known latex allergy, the simple act of being wrapped in a latex‑lined sheet could set off a flare.
Infections and immune shifts
Sometimes the infection itself—not the treatment—stimulates an overactive immune response. Viral or bacterial agents can prompt the body to release cytokines that, in turn, cause hives. The stress of fighting an illness also skews the immune system, making it more reactive to harmless stimuli.
What the rash looks like: Recognizing the symptoms
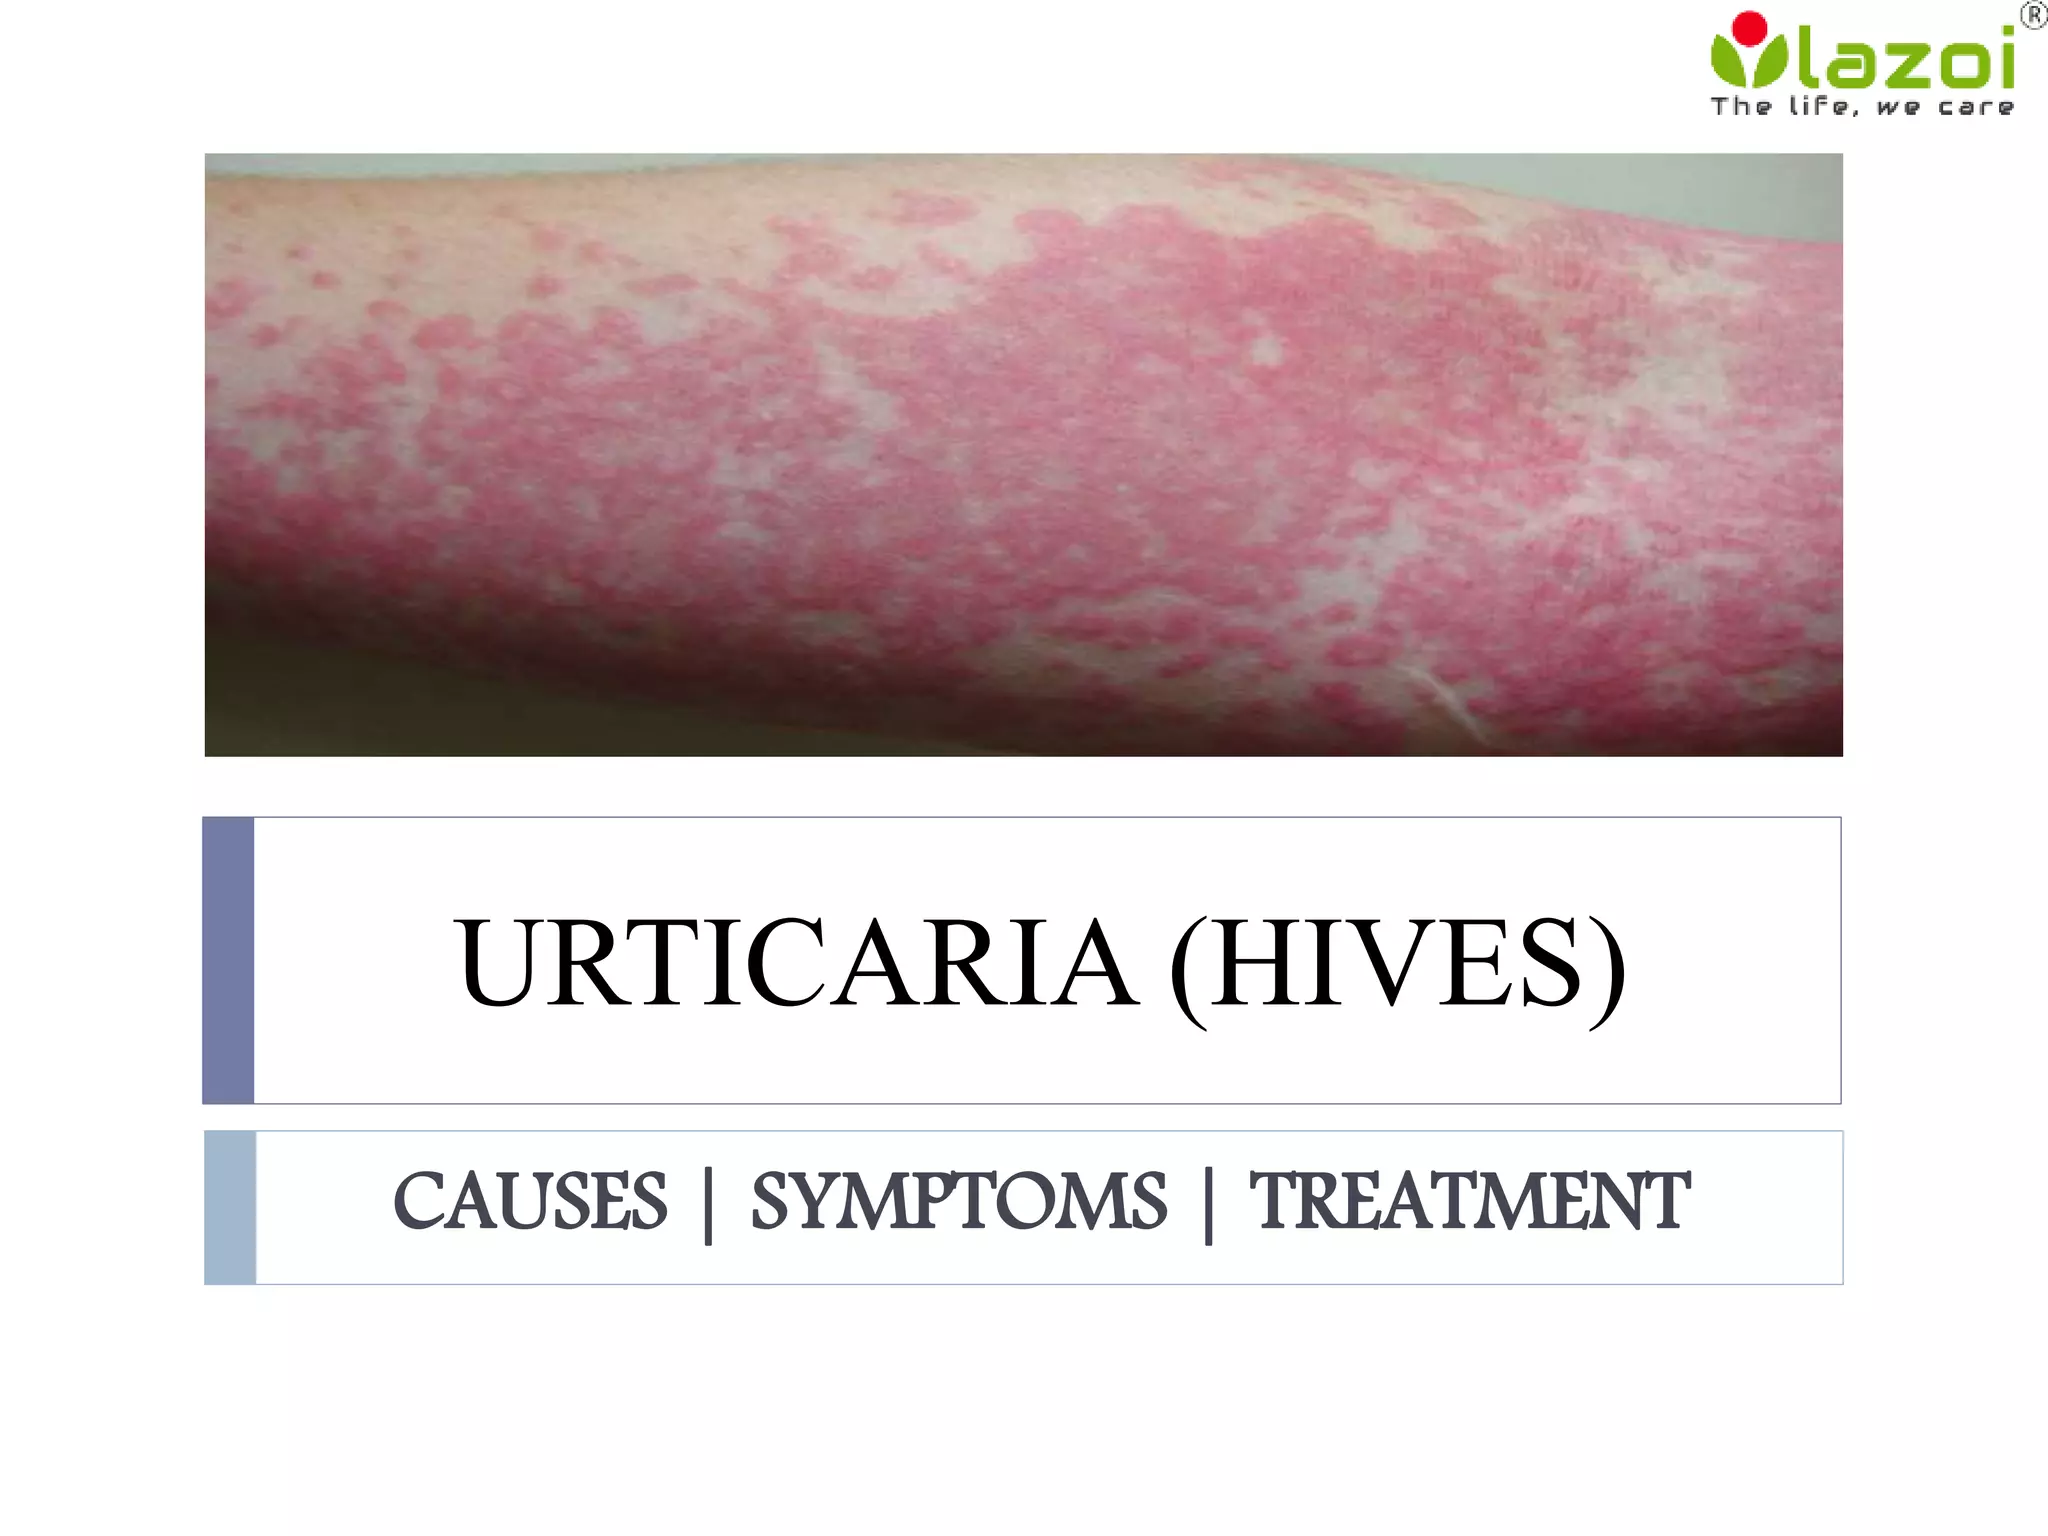
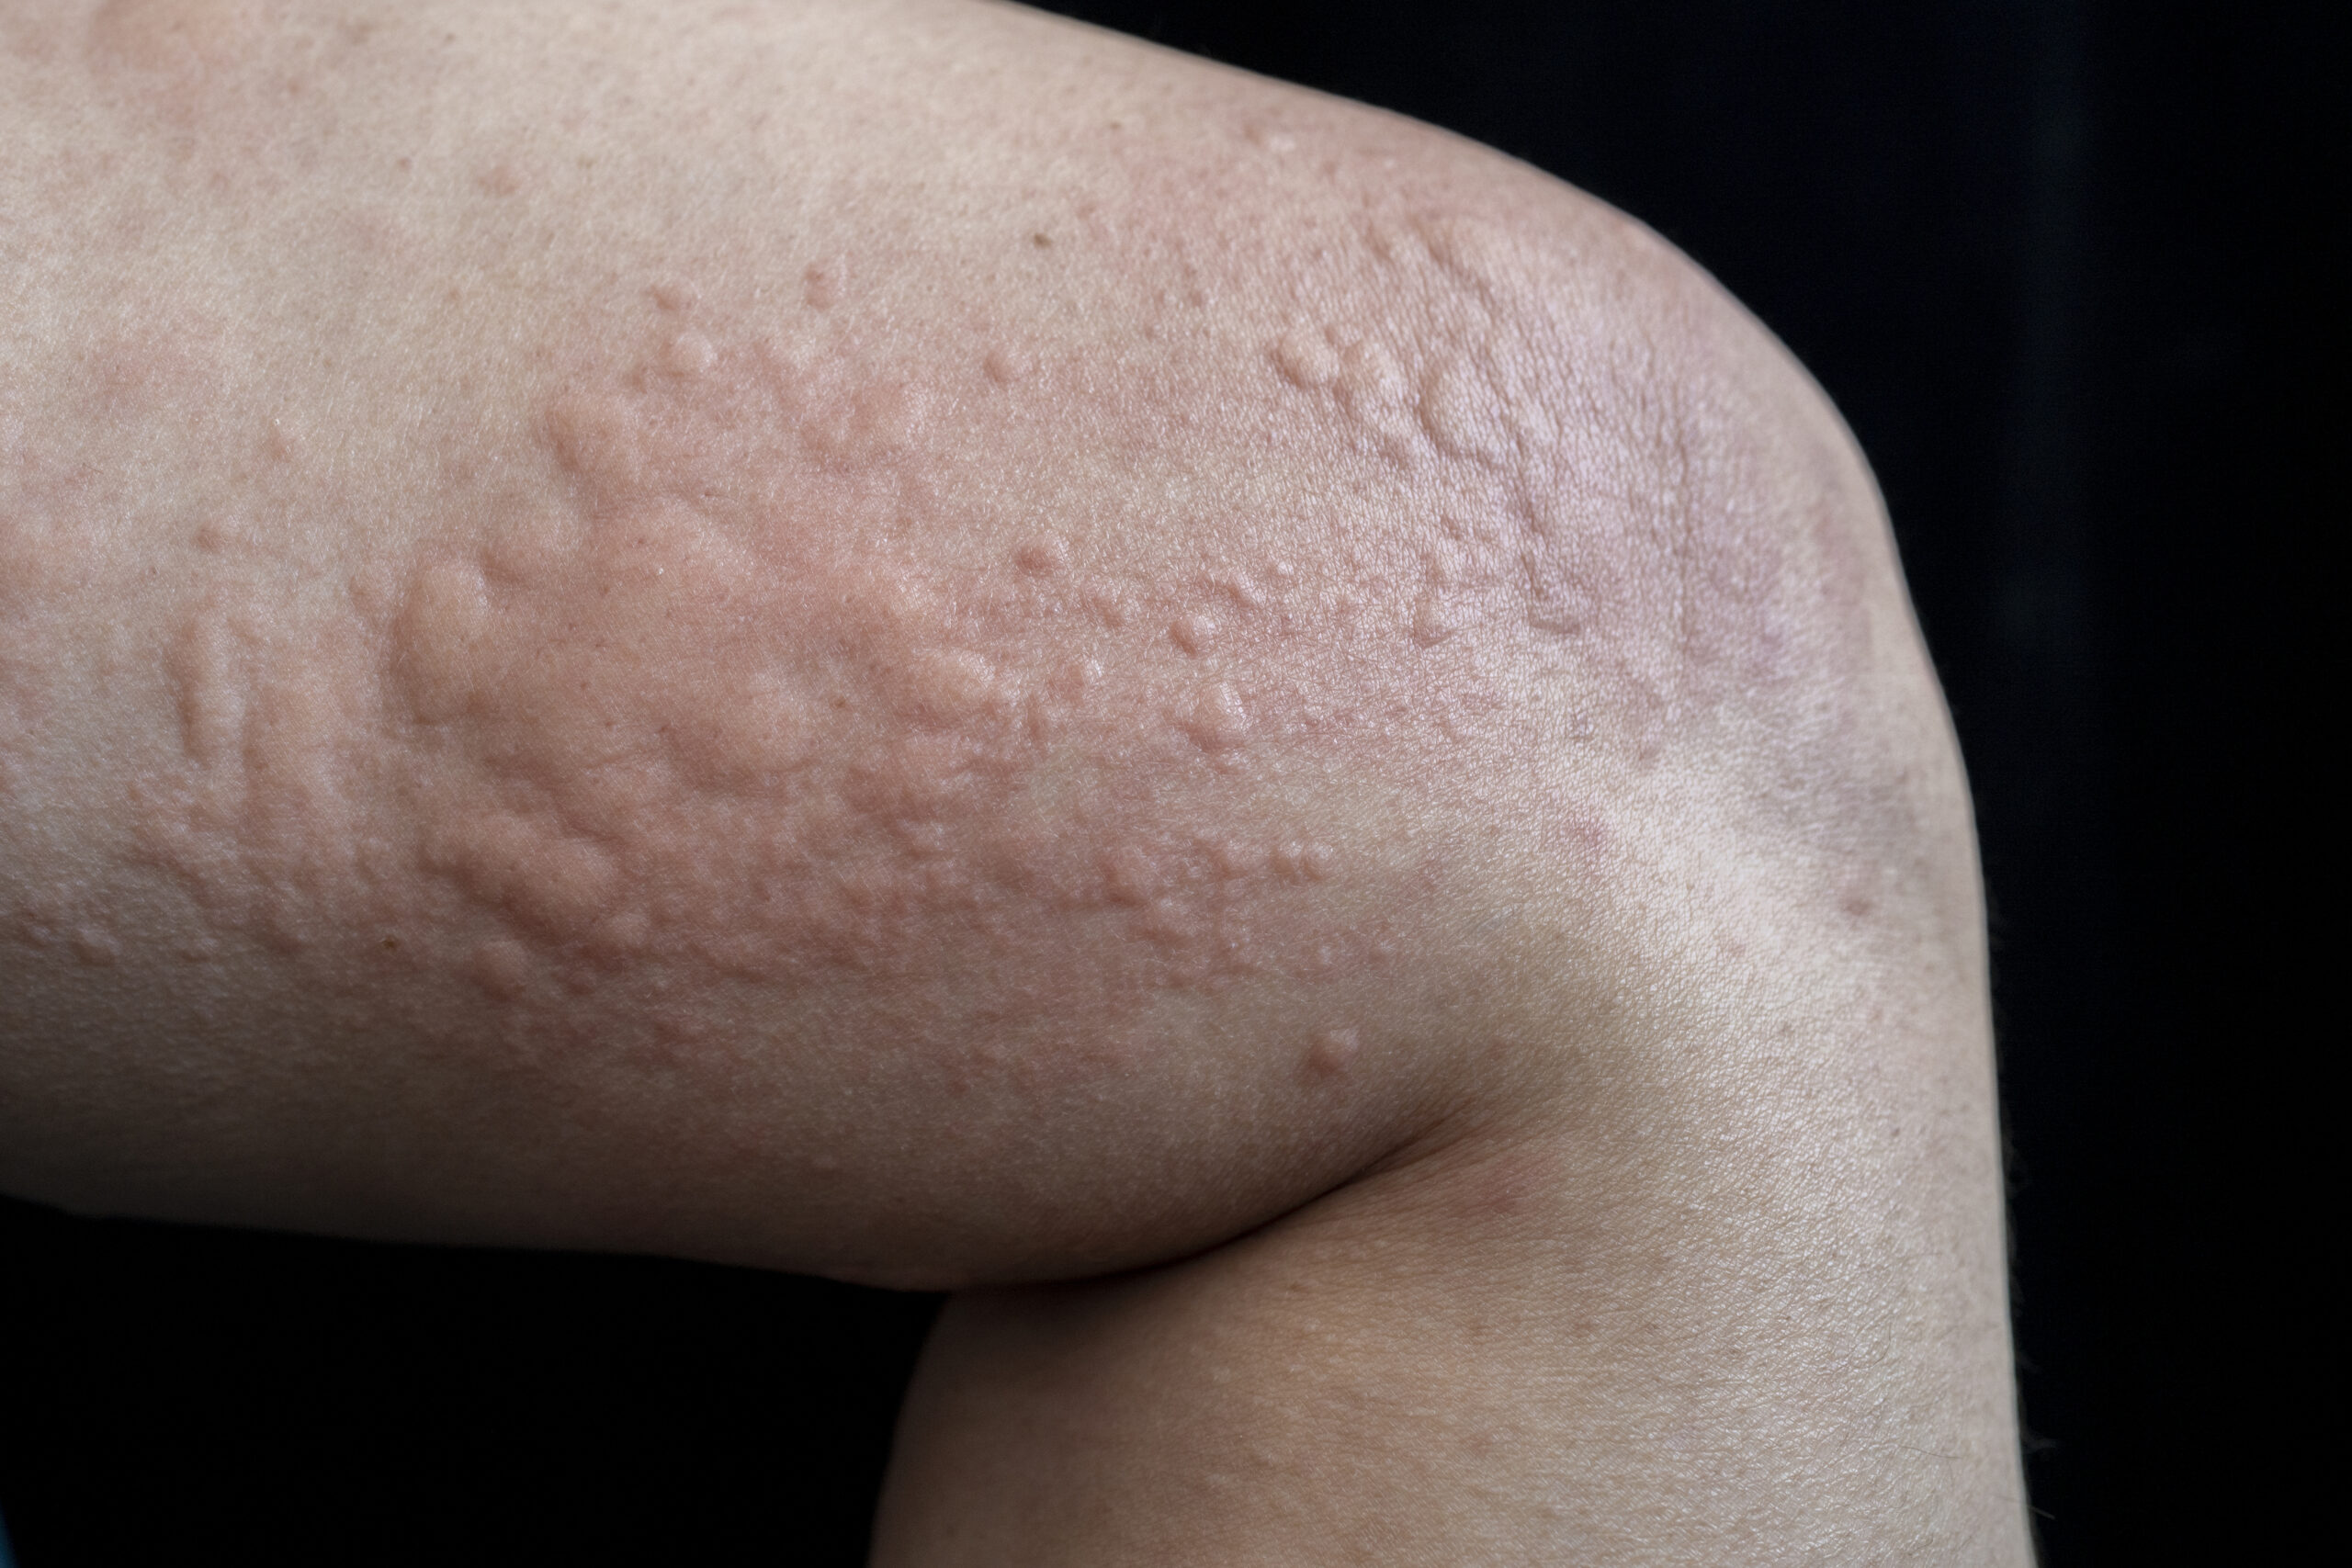
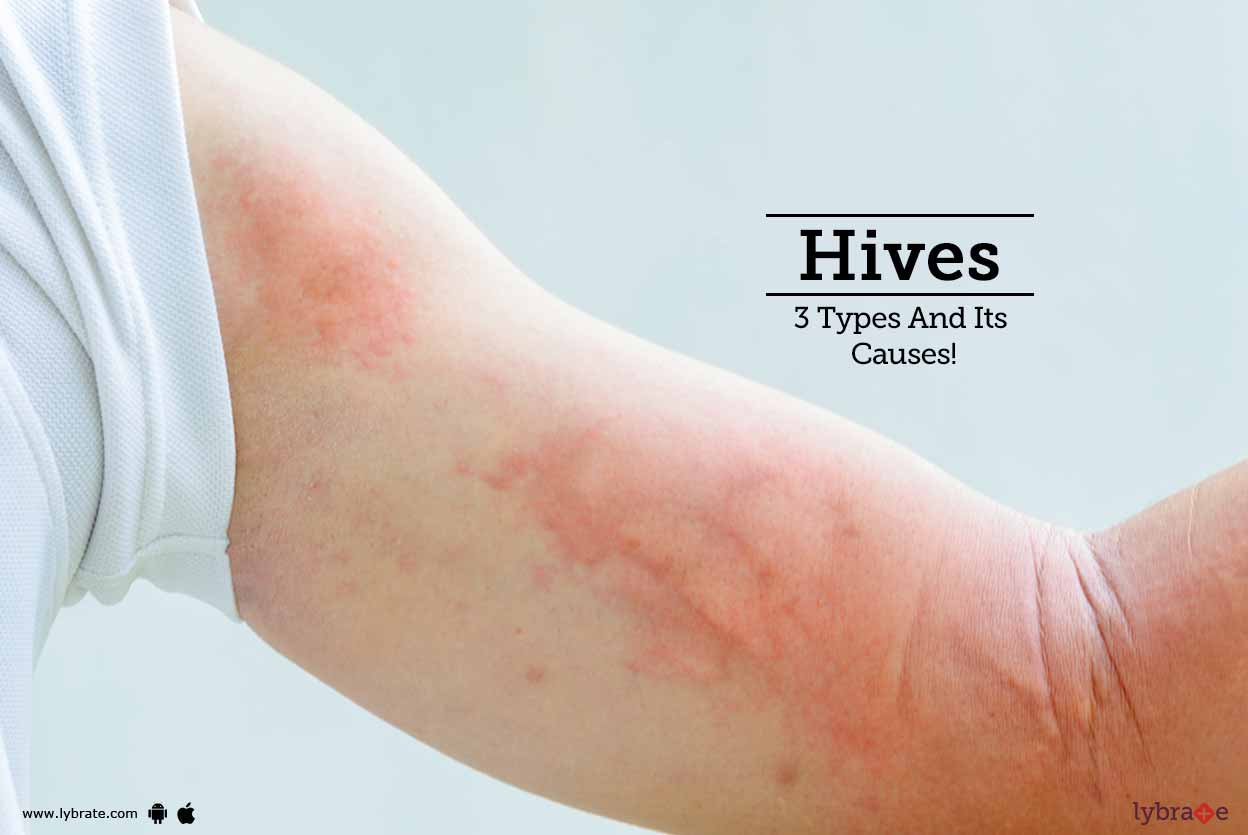
Hives after discharge usually appear as raised, pink or red welts that vary in size from a pinhead to a dinner‑plate. They may:
- Itch intensely, especially when scratched.
- Come and go within a few hours, only to reappear elsewhere.
- Coalesce into larger patches, sometimes called a “hive swarm.”
- Accompany mild swelling of the lips, eyelids, or hands—a sign to seek urgent care.
Unlike a rash caused by a medication‑induced drug eruption, hives typically lack scaling or crusting. Their fleeting nature is a key diagnostic clue.
First‑line treatment options
Most post‑hospital hives resolve with over‑the‑counter (OTC) measures, but the right approach depends on severity and timing.
Antihistamines
Non‑sedating antihistamines—cetirizine, loratadine, or fexofenadine—are the go‑to for daytime relief. For nighttime itching, a diphenhydramine dose can help you sleep, though it may cause drowsiness the next day. Start with the standard adult dose; if the welts persist after 24 hours, a doctor may double the dose.
When steroids become necessary
Short courses of oral corticosteroids (prednisone 10‑20 mg daily) can break a stubborn flare that doesn’t respond to antihistamines. Topical steroids—hydrocortisone 1 % cream—are useful for isolated patches, but they won’t calm a widespread hive storm.
Adjuncts and home care
- Cool compresses: Apply a damp, cool cloth for 10‑15 minutes to soothe itching.
- Moisturizers: Fragrance‑free creams help protect the skin barrier, reducing irritation.
- Avoidance: Keep a diary of foods, soaps, and new products introduced during your stay to spot patterns.
Preventing future episodes
Prevention starts with clear communication. Ask the admitting team to list every medication you receive, including “as‑needed” doses. If you have a documented latex allergy, request latex‑free supplies before any procedure. After discharge, review the medication list with your pharmacist; sometimes a drug substitution can spare you a repeat reaction.
For those prone to chronic urticaria, a low‑histamine diet—cutting back on aged cheese, fermented soy, and certain seafood—might lower baseline sensitivity. While the evidence isn’t ironclad, many patients report fewer flare‑ups when they eliminate obvious triggers.
Frequently Asked Questions
- Can I be discharged with hives? Yes, if the rash is limited to mild, non‑swelling welts and responds to antihistamines. However, any swelling of the face, throat, or difficulty breathing warrants immediate medical attention.
- Do I need an allergy test after the episode? It’s advisable if you’ve never had a reaction before or if multiple drugs were involved. Skin prick testing or specific IgE blood work can pinpoint the offending agent.
- How long will the hives last? Acute hives usually resolve within 24‑48 hours after treatment. If they persist beyond six weeks, you may be entering the realm of chronic urticaria, which requires a different management plan.
- Should I avoid all hospital visits in the future? Not at all. Knowing your triggers and informing healthcare providers ahead of time dramatically reduces risk. Most hospitals have protocols for allergy‑aware care.