The Essential Nursing Guide to Managing Fracture Care
Fracture care can feel like a high‑stakes puzzle, especially when you’re juggling pain control, immobilization, and the ever‑present risk of complications. As a bedside nurse, you’re the constant in a chaotic scene, translating doctors’ orders into hands‑on actions that keep bones healing safely. This guide walks you through the most critical steps, from the first assessment to the moment the patient walks out the door with a solid plan for recovery.
Key Steps in Fracture Care
Every fracture case follows a predictable rhythm: assessment, stabilization, monitoring, and education. Mastering each phase reduces errors and boosts patient confidence. Below, each step is broken down into bite‑size actions you can apply during a shift.
1. Rapid Assessment
- Check for obvious deformities, swelling, and bruising.
- Ask the patient to describe the mechanism of injury; high‑energy trauma often signals hidden injuries.
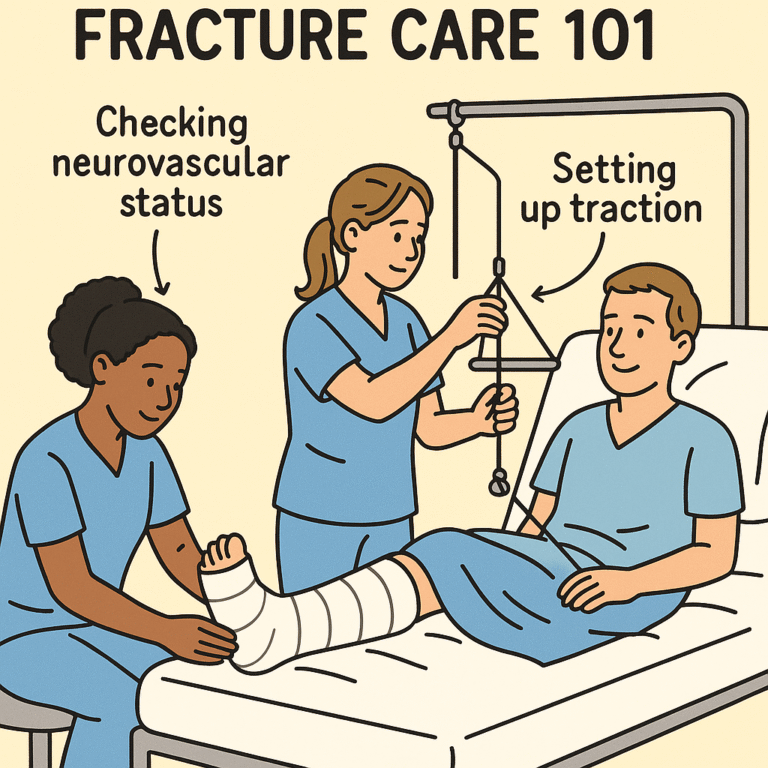
- Conduct a brief neurovascular check—pulses, capillary refill, and sensation in the distal extremity.
Document findings using the ABCDE framework (Airway, Breathing, Circulation, Disability, Exposure) as a safety net for any sudden changes.
2. Pain Management
Effective analgesia is more than a comfort measure; it prevents sympathetic spikes that can impair circulation. Follow the hospital’s multimodal protocol—often a combination of opioids, NSAIDs, and regional blocks. Remember to reassess pain every 30 minutes until the patient reports a tolerable level, typically a score of 3 or lower on a 0‑10 scale.
Understanding Common Fracture Types
Not all breaks are created equal. Knowing whether you’re dealing with a simple transverse fracture, a comminuted shard, or an open compound break shapes your nursing interventions.
Simple closed fractures usually need standard splinting and routine monitoring. Comminuted fractures—where the bone shatters into multiple pieces—require extra vigilance for swelling and compartment syndrome. Open fractures* present a direct portal to the outside world, demanding immediate sterile dressing, antibiotics, and urgent surgical consultation.
Initial Assessment and Pain Management
After the primary survey, you’ll often be the first to apply a splint or cast. Choose a material that balances rigidity with comfort—fiberglass is common, but plaster may be preferable for pediatric patients due to its moldability.
While you’re molding the device, keep the limb elevated to reduce edema. Elevation, combined with intermittent ice packs (15 minutes on, 20 minutes off), can shave minutes off swelling time, which in turn eases later physiotherapy.
Immobilization Techniques Every Nurse Should Know
Whether you’re using a splint, a temporary traction, or a definitive cast, the goal is to immobilize the fracture while preserving neurovascular integrity.
- Buddy taping for minor finger or toe fractures—align the injured digit alongside an adjacent one and secure with soft tape.
- U‑slab splinting for forearm or tibial fractures—wrap the injured limb from just above the fracture site to the distal end, ensuring the joint above remains mobile.
- Traction in cases like femur or humeral shaft breaks—monitor the weight and alignment every hour, watching for signs of loosening.
Always check that the immobilization device isn’t too tight; a snug fit that compromises circulation is a fast track to compartment syndrome.
Monitoring for Complications
Complications rarely announce themselves politely. Keep a watchful eye for:
- Compartment syndrome—pain out of proportion, tense swelling, and a painful passive stretch.
- Deep vein thrombosis (DVT)—calf tenderness, swelling, or a sudden change in skin temperature.
- Infection in open fractures—redness, foul odor, or increasing drainage.
If any of these signs appear, activate the rapid response team and document the timeline meticulously. Early detection can mean the difference between a smooth recovery and a prolonged hospital stay.
Patient Education and Discharge Planning
Discharge isn’t the end of fracture care; it’s the start of self‑management. Your teaching points should be clear, concise, and tailored to the patient’s health literacy.
Key messages include:
- How to keep the immobilization device dry and clean.
- Signs of complications that warrant a call to the clinic.
- The importance of scheduled follow‑up X‑rays—usually at 2‑week and 6‑week intervals.
- Basic exercises for maintaining joint mobility without jeopardizing the healing bone.
Providing a printed checklist can reinforce verbal instructions, especially for older adults or those with limited English proficiency.
FAQs
What is the best way to assess neurovascular status in a patient with a cast?
Check distal pulses (radial, dorsalis pedis), assess capillary refill (under 2 seconds is normal), and ask the patient to move toes or fingers. Document any changes immediately.
How long should a nurse wait before removing a splint for a routine check?
Most protocols allow a brief “window” of 10‑15 minutes after the first 24‑hour period, provided the patient’s pain is controlled and neurovascular status is stable.
When is it appropriate to start passive range‑of‑motion exercises?
Typically after the initial inflammatory phase—about 48‑72 hours post‑injury—once the physician signs off and pain is manageable. Always follow the surgeon’s specific timeline.