What’s Inside the 6‑Hour Sepsis Bundle and Why It Matters
When a patient’s infection spirals into sepsis, every minute counts. The 6Hour Sepsis Bundle was created to squeeze the most life‑saving actions into the first half‑day of care, giving clinicians a clear checklist while the body fights a runaway inflammatory response. Understanding exactly what belongs in that bundle—and why the clock is relentless—helps hospitals move from “nice‑to‑have” to “must‑do” in real time.
6Hour Sepsis Bundle: What’s Included
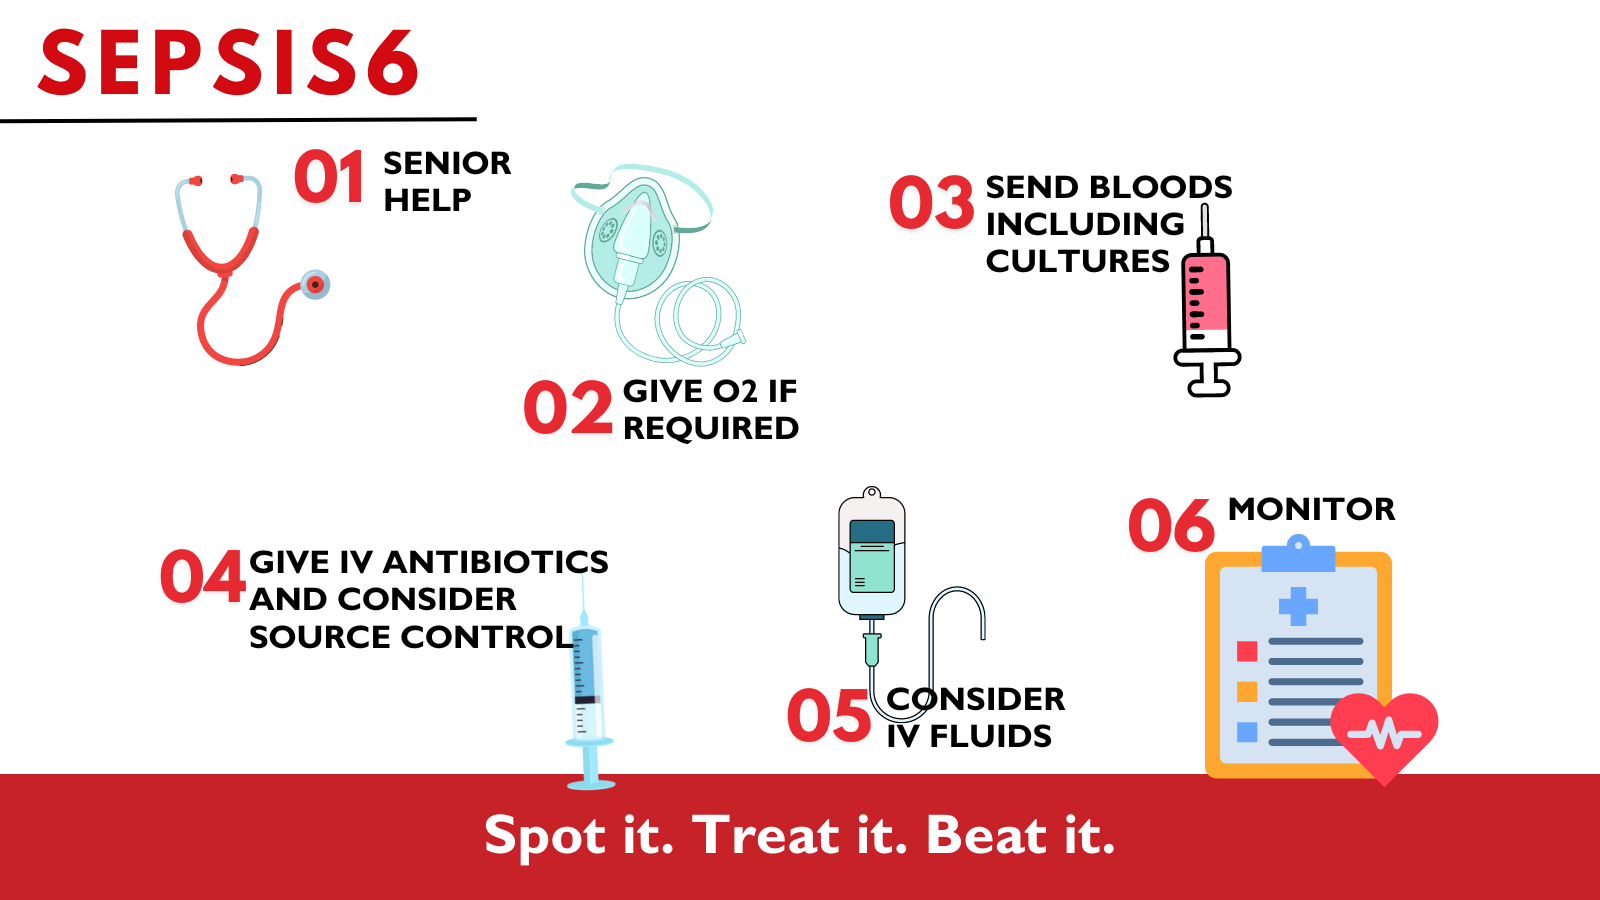
Think of the bundle as a rapid‑response kit. The core elements are meant to be completed within six hours of recognizing sepsis, and they fall into three practical categories: assessment, treatment, and reassessment.
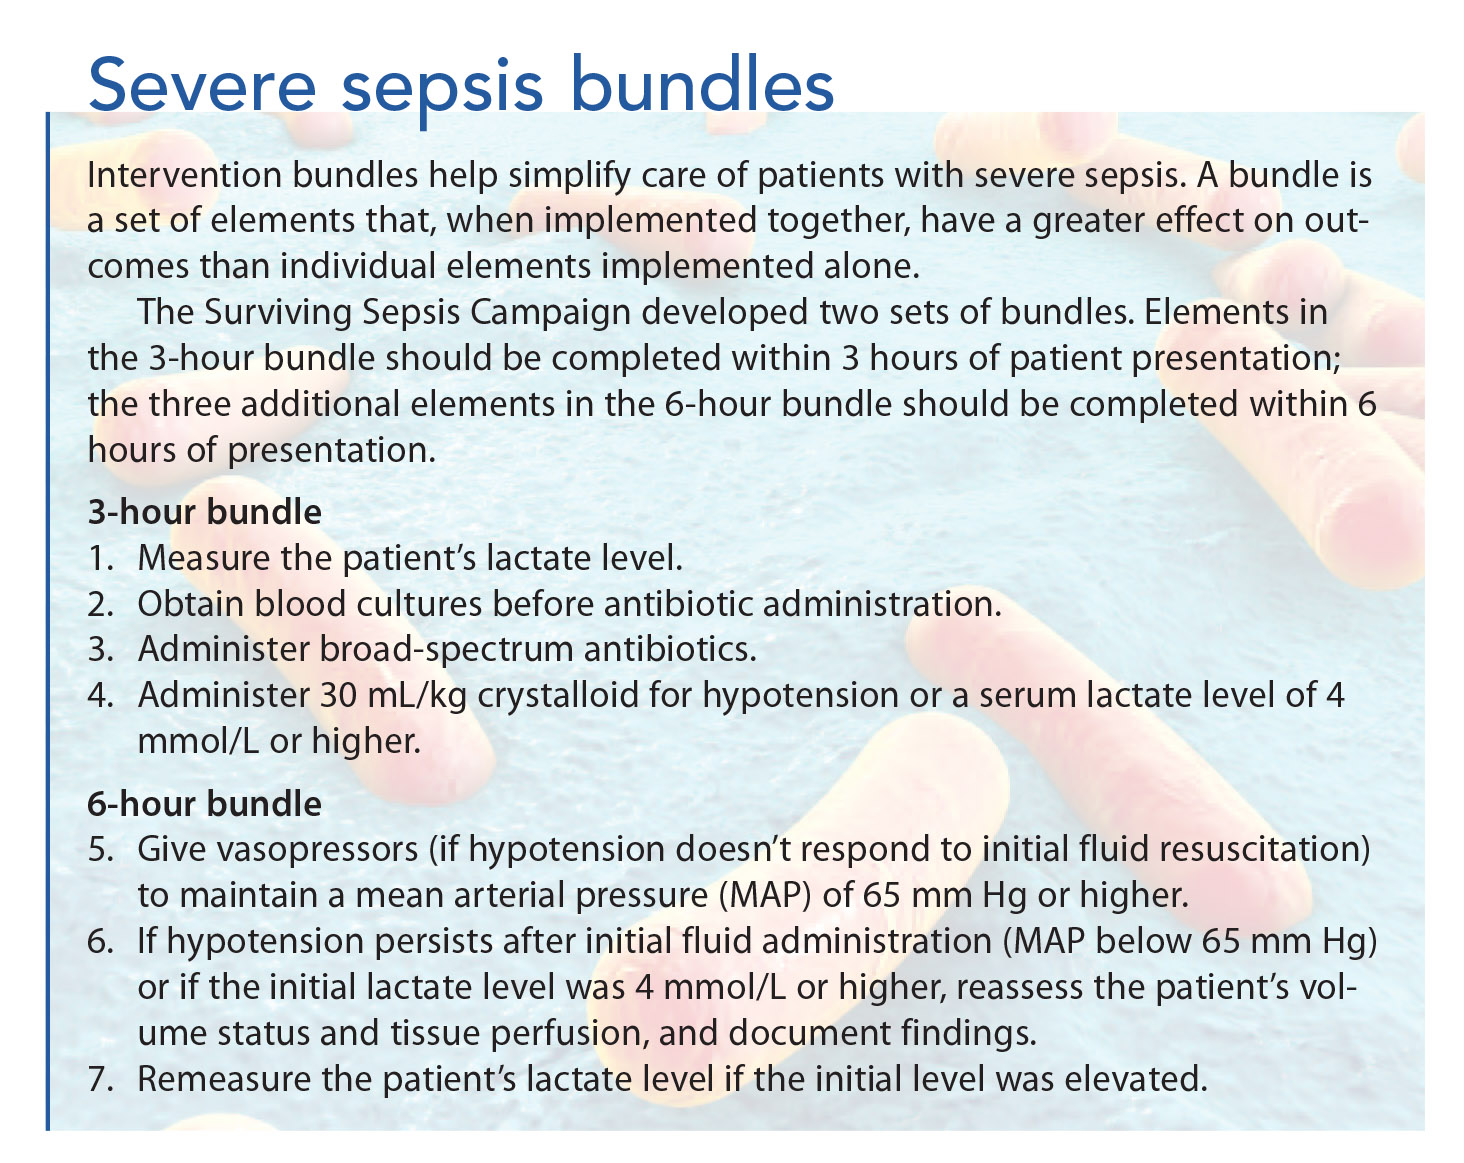
- Measure serum lactate. An elevated lactate (>2 mmol/L) flags tissue hypoperfusion even before blood pressure drops.
- Obtain blood cultures before antibiotics. Drawing at least two sets from separate sites improves pathogen identification without delaying therapy.
- Administer broad‑spectrum antibiotics within the first hour. Early, appropriate antimicrobial coverage is the single most influential factor in survival.
- Start 30 mL/kg crystalloid fluid bolus. This is required for patients with hypotension or lactate ≥4 mmol/L, aiming to restore intravascular volume.
- Apply vasopressors if MAP stays below 65 mmHg after fluids. Norepinephrine is the first‑line choice, titrated to maintain adequate organ perfusion.
- Re‑measure lactate. A repeat draw after initial resuscitation checks whether tissue oxygenation is improving.
- Document a clear reassessment plan. By six hours, the team should have a definitive diagnosis, ongoing source‑control steps, and a tailored organ‑support strategy.
These steps are intentionally concise; the goal is to avoid analysis paralysis while still covering the evidence‑based foundations of sepsis care.
Why Timely Completion Saves Lives
Sepsis isn’t a static condition—it can double its mortality risk with each hour that treatment is delayed. Studies that track bundle compliance consistently show a drop in in‑hospital death rates, often by 15‑20 % compared with patients who receive care later. The reason is two‑fold.
First, early antibiotics halt bacterial proliferation before toxins overwhelm the immune system. Second, rapid fluid resuscitation and vasopressor support preserve blood flow to vital organs, buying time for the body’s defenses to regroup. Even a modest reduction in lactate after the initial bolus is a strong predictor that the patient is trending toward stability.
Beyond the numbers, the bundle creates a shared mental model across the emergency department, intensive care unit, and ward staff. When everyone knows, “we have six hours to get these labs, meds, and fluids in,” communication improves, and missed steps become rare.
Common Hurdles in Bundle Delivery
Implementing the 6Hour Sepsis Bundle isn’t automatic. Many hospitals hit roadblocks that turn a simple checklist into a logistical nightmare.
- Lab turnaround time. Lactate results can linger if point‑of‑care testing isn’t available, delaying the decision to push fluids.
- Antibiotic stewardship concerns. Clinicians sometimes hesitate to start broad‑spectrum agents before cultures, fearing resistance.
- Fluid overload risk. Patients with heart failure or chronic kidney disease may need a gentler approach, which can complicate the “30 mL/kg” rule.
- Staffing gaps. Night shifts or rural settings often lack the dedicated sepsis teams that larger centers enjoy.
Recognizing these friction points early lets quality‑improvement teams design work‑arounds—like standing orders for lactate, rapid‑response pharmacy carts, or protocol‑driven fluid titration charts.
Tips for Streamlining Your Process
Here are a few practical moves that have helped other institutions shave minutes off their bundle times.
- Place lactate point‑of‑care devices at bedside in the emergency department and critical care units.
- Pre‑authorize a “sepsis antibiotic bundle” in the pharmacy system, so the first dose can be pulled and administered without a separate order.
- Use electronic health record alerts that fire when the first sepsis criteria are met, automatically populating the order set.
- Assign a dedicated “sepsis champion” per shift to verify that cultures, labs, and fluids are on track.
- Run monthly mock drills; they reveal hidden delays and reinforce the six‑hour timeline for the whole team.
When these steps become part of the unit’s culture, the 6Hour Sepsis Bundle shifts from a hopeful guideline to a reliable safety net.
Frequently Asked Questions
What if the patient’s lactate is normal on admission?
Even with a normal lactate, the bundle still calls for early antibiotics and fluid assessment if other sepsis signs are present. Lactate is a trigger, not an exclusion.
Can the fluid volume be adjusted for a patient with heart failure?
Yes. The 30 mL/kg target is a guideline; clinicians should balance the risk of overload with the need for perfusion, often using smaller boluses and closer hemodynamic monitoring.
How does the bundle differ from the “3‑Hour Bundle”?
The 3‑Hour version focuses on the initial steps—lactate, cultures, antibiotics, and fluids—while the 6‑Hour bundle adds repeat lactate, vasopressor initiation, and a formal reassessment plan.
Is it okay to start antibiotics before cultures if time is critical?
Ideally, cultures are drawn first, but if a delay would push antibiotics beyond the one‑hour window, it’s better to give the medication and obtain cultures as soon as feasible.