Understanding T4b Breast Cancer: Treatment Options Explained
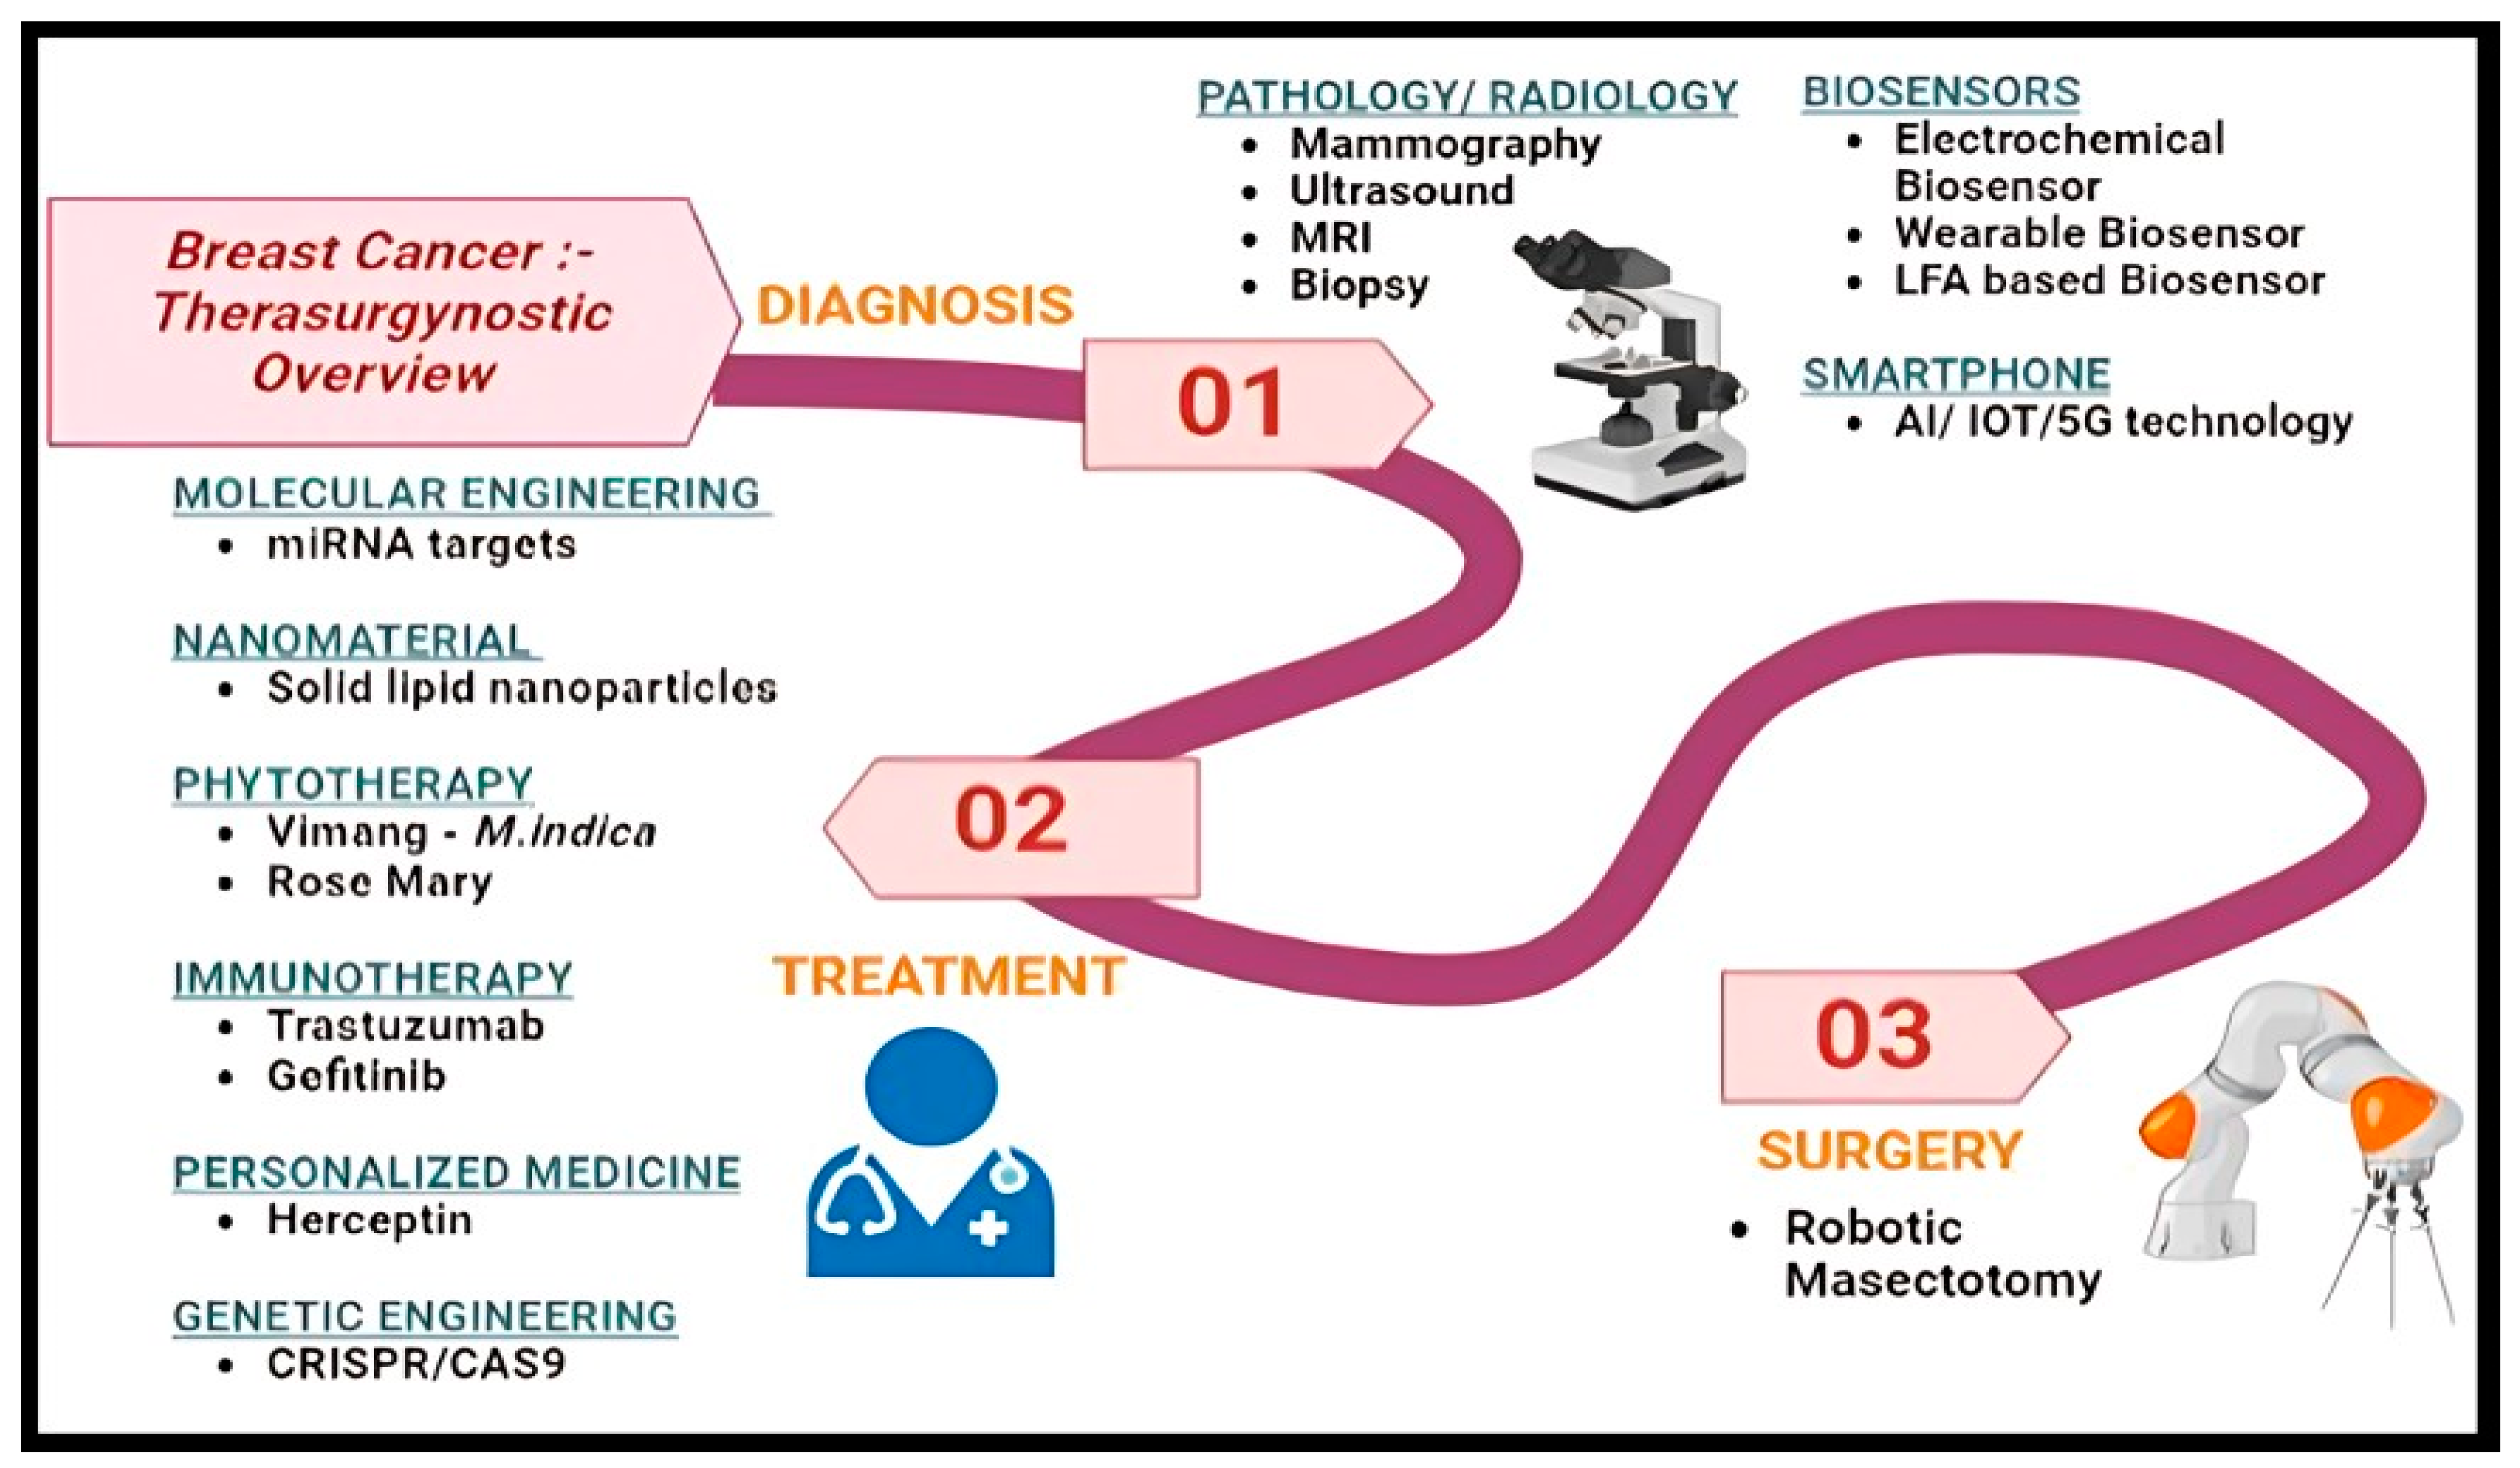
When a diagnosis of T4b breast cancer lands on a patient’s doorstep, the word “treatment” instantly conjures a maze of possibilities. T4b breast cancer treatment options span surgery, radiation, systemic therapies, and sometimes experimental trials—all aimed at controlling a tumor that has invaded the skin or caused ulceration. Below, we break down each avenue in plain language so you can weigh the benefits, risks, and realistic expectations.
What Does T4b Mean in Breast Cancer Staging?
The “T” in the TNM system describes the size and extent of the primary tumor. T4 indicates a tumor of any size that has broken through the breast’s natural barrier, while the “b” subtype specifies direct extension to the skin, often manifesting as edema, ulceration, or a satellite nodule. This classification signals an advanced local stage, but it does not yet imply distant spread (M0). Knowing the exact definition helps clinicians tailor a multimodal approach.
Surgical Strategies: When Removing the Tumor Is Feasible
Even with skin involvement, surgery can remain a cornerstone of care, especially if the tumor is still resectable.
- Modified radical mastectomy – removal of the entire breast tissue, underlying muscle fascia, and regional lymph nodes. This is the most common choice for T4b because it ensures clear margins despite skin changes.
- Skin‑sparing mastectomy with immediate reconstruction – viable when the skin involvement is limited to a small area that can be excised while preserving enough healthy skin for a cosmetic outcome.
- Lumpectomy (breast‑conserving surgery) – rarely an option for T4b, but in select cases where the skin ulceration is focal and margins can be guaranteed, it may be considered alongside aggressive radiation.
Each surgical route demands a thorough discussion about potential complications, such as wound healing delays, especially when radiation follows.
Radiation Therapy: Targeting Residual Cells
Post‑operative radiation is almost always recommended for T4b disease, even after a mastectomy, because microscopic cancer cells frequently linger in the chest wall or skin.
- Post‑mastectomy radiation therapy (PMRT) – delivers doses to the chest wall and regional lymph nodes, reducing local recurrence by 20‑30% in high‑risk patients.
- Regional nodal irradiation – extends the field to cover the supraclavicular and internal mammary nodes, which are at higher risk when the tumor invades the skin.
- Advanced techniques – intensity‑modulated radiation therapy (IMRT) and proton therapy can spare nearby organs (heart, lungs) while maintaining dose intensity on the tumor bed.
Systemic Therapies: Going Beyond the Breast
Because T4b denotes an aggressive local disease, systemic treatment often starts before surgery (neoadjuvant) to shrink the tumor and assess chemosensitivity.
- Neoadjuvant chemotherapy – typically a combination of anthracyclines and taxanes; it can downstage the tumor, making surgery easier.
- Targeted therapy for HER2‑positive tumors – agents like trastuzumab and pertuzumab have transformed outcomes, cutting recurrence risk dramatically.
- Hormone therapy – for estrogen‑ or progesterone‑receptor‑positive cancers, aromatase inhibitors or tamoxifen are added after surgery.
- Immunotherapy – checkpoint inhibitors (e.g., pembrolizumab) are now approved for triple‑negative breast cancers with high PD‑L1 expression, even in the neoadjuvant setting.
Emerging Options and Clinical Trials
Patients with T4b disease are often encouraged to explore clinical trials, especially when standard regimens fall short. Current investigations include antibody‑drug conjugates targeting novel antigens, CAR‑T cell therapy adapted for solid tumors, and combination regimens that pair immunotherapy with PARP inhibitors for BRCA‑mutated cancers. Enrollment not only offers access to cutting‑edge drugs but also contributes valuable data for future treatment guidelines.
Managing Side Effects and Quality of Life
Intensive multimodal therapy can take a toll. Proactive symptom management—such as skin‑care protocols for radiation‑induced dermatitis, lymphedema monitoring, and psychosocial support—helps maintain daily function.
- Skin care – gentle cleansers, moisturizers, and protective dressings reduce radiation burns.
- Lymphedema prevention – compression garments and supervised exercises keep arm swelling in check after lymph node removal.
- Emotional health – counseling, support groups, and survivorship programs address anxiety, body image concerns, and the fear of recurrence.
Putting It All Together: A Personalized Plan
Choosing the right blend of surgery, radiation, and systemic therapy is rarely a one‑size‑fits‑all decision. Oncologists weigh tumor biology (HER2, hormone receptors), patient comorbidities, and personal preferences. A typical pathway might begin with neoadjuvant chemotherapy, proceed to a modified radical mastectomy, followed by PMRT and targeted hormonal therapy. Yet for some, a skin‑sparing mastectomy with immediate reconstruction and a clinical‑trial‑only regimen may be preferable. Open communication with the multidisciplinary team ensures that the final plan aligns with both medical goals and the patient’s lifestyle.
Frequently Asked Questions
Can T4b breast cancer be cured?
While T4b indicates an advanced local stage, many patients achieve long‑term remission when a comprehensive, tailored treatment plan is followed. Cure rates depend on tumor biology, response to therapy, and absence of distant metastasis.
Is breast‑conserving surgery ever an option for T4b?
It’s uncommon, but if the skin involvement is limited to a small, excisable area and clear margins can be guaranteed, a lumpectomy paired with extensive radiation may be considered.
What role do clinical trials play in T4b treatment?
Trials often test newer drugs or combinations that aren’t yet standard of care. Participation can provide access to potentially more effective therapies, especially for patients whose tumors have aggressive features or lack response to conventional treatments.
How long is the typical treatment timeline?
From diagnosis to the end of adjuvant therapy, the process can span 6‑12 months, depending on the need for neoadjuvant chemotherapy, surgical recovery, and the duration of radiation and systemic treatments.