Luminal A vs Luminal B: What HER2‑Positive Breast Cancer Means
Why the Subtype Labels Matter
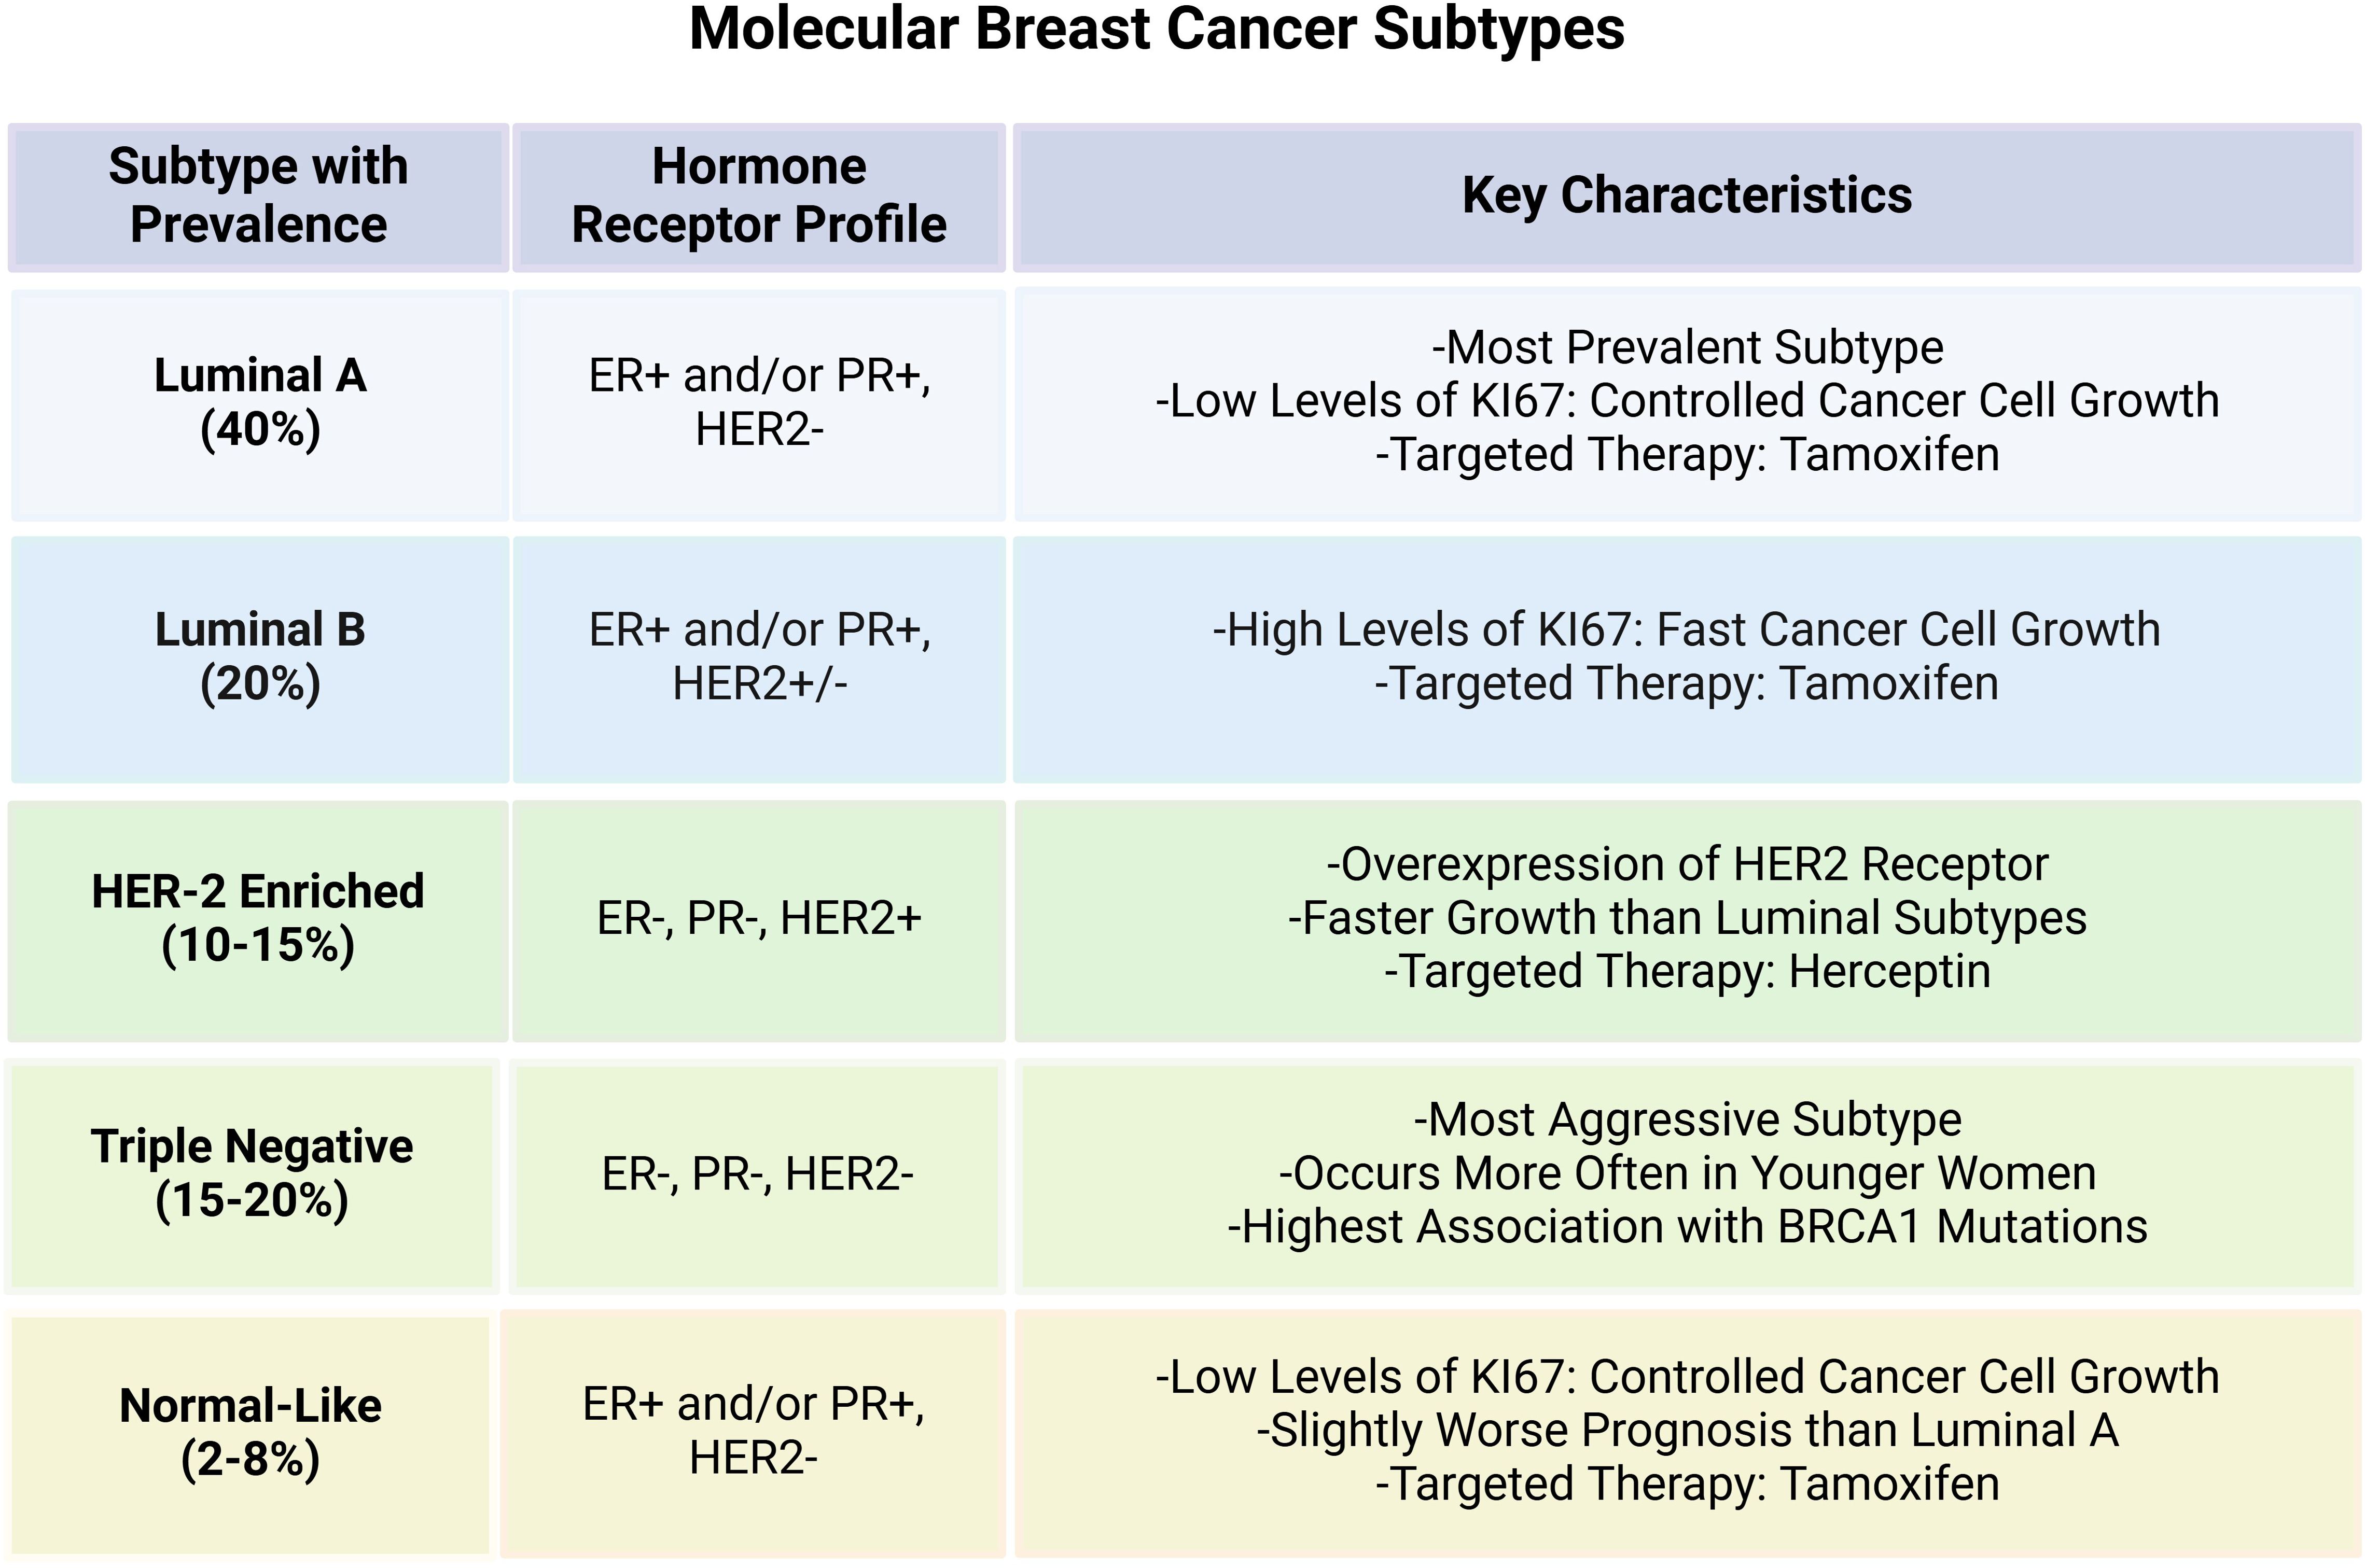
When a pathologist reports a breast tumor as “luminal,” they’re referring to cancers that express hormone receptors—estrogen (ER) and/or progesterone (PR). Within this broad group, the two most common sub‑categories are Luminal A and Luminal B. The distinction isn’t just academic; it guides treatment choices, informs prognosis, and—crucially—intersects with HER2 status, the “plus” in HER2‑positive breast cancer.
In short, a luminal tumor can be HER2‑negative, HER2‑positive, or even display mixed features. Understanding how Luminal A and Luminal B differ when HER2 is over‑expressed helps patients and clinicians navigate a more nuanced therapeutic landscape.
Core biological differences
Both subtypes share hormone‑receptor positivity, yet they diverge on several molecular fronts:
- Ki‑67 proliferation index: Luminal A tumors typically have a low Ki‑67 (<20%), indicating slower cell division. Luminal B cancers often show higher Ki‑67, reflecting a more aggressive growth pattern.
- Gene expression profiles: Luminal A aligns closely with a “classic” estrogen‑driven signature, while Luminal B includes additional genes linked to cell cycle progression.
- HER2 expression: By definition, Luminal A is usually HER2‑negative, but Luminal B can be either HER2‑negative or HER2‑positive. The HER2‑positive subset is the focus when we talk about HER2‑positive breast cancer.
These molecular hallmarks translate into real‑world differences in how tumors behave and respond to therapy.
Implications of HER2 positivity
HER2 (human epidermal growth factor receptor 2) is a protein that, when over‑expressed, drives rapid tumor growth. Targeted agents such as trastuzumab, pertuzumab, and newer antibody‑drug conjugates have dramatically improved outcomes for HER2‑positive patients.
When HER2 positivity appears in a luminal context, it creates a hybrid phenotype: the tumor still relies on estrogen signaling, but it also harnesses the HER2 pathway. This dual dependence opens the door to combined endocrine and HER2‑directed therapies.
Treatment strategies for each subtype
Luminal A, HER2‑negative usually receives endocrine therapy alone (tamoxifen or aromatase inhibitors) after surgery, sometimes followed by radiation. The prognosis is generally favorable, with lower recurrence rates.
Luminal B, HER2‑negative often adds chemotherapy to endocrine therapy because of the higher Ki‑67 and greater risk of early recurrence.
Luminal B, HER2‑positive is where treatment becomes more intricate. Standard practice typically includes:
- Neoadjuvant or adjuvant chemotherapy combined with HER2‑targeted agents (e.g., trastuzumab ± pertuzumab).
- Concurrent endocrine therapy to suppress estrogen signaling.
- Consideration of treatment duration: HER2‑targeted therapy is often given for a year, but ongoing trials are exploring shorter or extended schedules.
Clinical trials have shown that adding HER2‑directed drugs to endocrine therapy can improve disease‑free survival even when chemotherapy is omitted, though this approach is still being refined.
Prognostic outlook
Historically, HER2‑positive cancers were associated with poorer outcomes, but modern HER2‑targeted regimens have narrowed that gap. Nevertheless, luminal B, HER2‑positive tumors tend to have a slightly higher risk of recurrence compared to pure Luminal A, HER2‑negative disease.
Key prognostic factors include:
- Stage at diagnosis (tumor size and nodal involvement).
- Ki‑67 level—higher indices correlate with more aggressive behavior.
- Response to neoadjuvant therapy; achieving a pathologic complete response (pCR) is linked to better long‑term outcomes.
Patients who achieve pCR after combined HER2‑targeted and chemotherapy regimens often enjoy survival rates comparable to those with less aggressive subtypes.
Practical tips for patients navigating the diagnosis
Receiving a pathology report that mentions “Luminal B, HER2‑positive” can feel overwhelming. Here are three practical steps to consider:
- Ask for a clear explanation of the biomarkers—specifically ER, PR, HER2, and Ki‑67. Knowing the exact numbers helps you understand why certain drugs are recommended.
- Discuss the treatment sequence with your oncologist. In many cases, a short course of neoadjuvant therapy is followed by surgery and then tailored adjuvant treatment, but the exact plan can vary based on tumor size and personal health.
- Explore clinical trial options. Ongoing studies are testing newer HER2‑targeted agents and endocrine‑only approaches for selected patients, which may be relevant if you prefer to avoid chemotherapy.
Future directions
Research continues to dissect the luminal‑HER2 overlap. Emerging biomarkers—such as PIK3CA mutations and circulating tumor DNA—could eventually refine risk stratification beyond the traditional luminal A/B classification.
Moreover, novel agents like tucatinib (a HER2‑specific tyrosine kinase inhibitor) and antibody‑drug conjugates are expanding the therapeutic arsenal, offering hope for patients whose disease recurs despite standard therapy.
Frequently Asked Questions
Is Luminal B always more aggressive than Luminal A? Generally, yes. Luminal B tumors tend to grow faster (higher Ki‑67) and have a higher likelihood of recurrence, especially when HER2 is positive.
Can I avoid chemotherapy if I have Luminal B, HER2‑positive cancer? In some cases, clinical trials have shown benefit from combining HER2‑targeted therapy with endocrine treatment alone, but chemotherapy remains the standard for most patients to maximize the chance of complete response.
How long will I need HER2‑targeted therapy? The typical recommendation is one year of trastuzumab, with or without pertuzumab, though the exact duration may be adjusted based on individual risk factors and emerging evidence.
Does HER2 positivity affect hormone‑therapy effectiveness? HER2 over‑expression can confer some resistance to endocrine therapy, which is why combining HER2‑targeted agents with hormone blockers is often more effective than hormone therapy alone.