How to Spot Ascites: Exam Techniques and Diagnostic Tips
When a patient presents with abdominal swelling, clinicians often suspect ascites—fluid accumulation in the peritoneal cavity. Recognizing and confirming ascites through a focused physical exam is critical before ordering imaging or invasive procedures. Below, we outline practical exam techniques and diagnostic steps that help distinguish true ascites from other causes of abdominal distension.
Ascites Physical Exam Techniques & Diagnosis
In a busy clinic, you’ll need a streamlined approach that balances thoroughness with efficiency. The following checklist covers the most reliable bedside maneuvers, followed by the key diagnostic work‑up.
1. Inspection
- Abdominal contour: Look for a smooth, distended belly with a subtle, convex contour. Ascitic fluid often creates a uniform fullness rather than localized bulging.
- Skin changes: Note any peripheral edema, bruising, or signs of chronic liver disease (e.g., jaundice, spider angiomata).
- Visible veins: Ascites can accentuate abdominal veins; observe for engorgement that may suggest portal hypertension.
2. Palpation
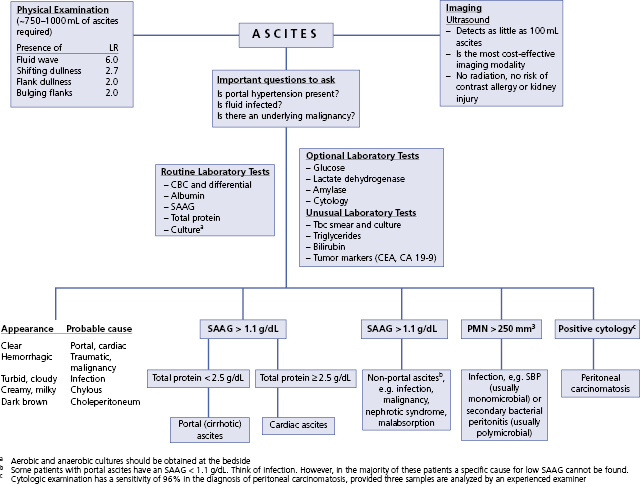
- Shifting dullness: With the patient supine, tap the right upper quadrant until a dull sound is heard. Then shift the patient’s head down. If the sound becomes more resonant, fluid has shifted, confirming ascites.
- Fluid wave: While the patient stands, gently strike the left lower quadrant and feel for a wave transmitted to the right. A clear wave indicates a significant fluid volume.
- Pitting edema: Press the heel of the foot; if the indentation persists for more than 30 seconds, fluid overload is likely present.
- Hepatojugular reflux: Apply firm pressure to the liver edge for 10–15 seconds while observing jugular venous pressure. A rise in jugular pulse suggests elevated intrabdominal pressure.
3. Auscultation and Percussion
- Peritoneal fluid percussion: Light taps over the abdomen should produce a resonant tone if fluid is present; dullness over the liver indicates hepatic congestion.
- Respiratory sounds: Check for diminished breath sounds on the left side due to diaphragmatic elevation.
Diagnostic Confirmation
While the physical exam is highly sensitive, confirming ascites and determining its etiology often requires further investigations.
Imaging
- Ultrasound: The gold standard for quantifying fluid volume and visualizing liver parenchyma or portal veins.
- CT scan: Useful in complex cases or when malignancy is suspected.
Paracentesis
A diagnostic tap is both confirmatory and therapeutic. Fluid analysis provides vital clues:
- Appearance: Clear, straw‑colored fluid is typical; cloudy or bloody fluid raises suspicion for infection or malignancy.
- Cell counts: Low leukocyte count (<250 cells/µL) points to transudate, while a high count suggests exudate or infection.
- Protein level: Low protein (<1.1 g/dL) indicates a transudate; higher levels (>2.5 g/dL) lean toward an exudate.
- Glucose, lactate dehydrogenase, and cytology: Help rule out bacterial peritonitis, tuberculosis, or malignancy.
Laboratory Tests
Baseline labs complement the physical exam:
- Liver function tests (AST, ALT, ALP, bilirubin): Elevated bilirubin or transaminases support liver disease.
- Albumin and coagulation profile: Low albumin and prolonged INR hint at advanced hepatic dysfunction.
- Kidney function (creatinine, BUN): Renal impairment can exacerbate fluid retention.
- Serum-ascites albumin gradient (SAAG): A SAAG >1.1 g/dL indicates portal hypertension as the underlying cause.
Differential Diagnosis
Remember that abdominal distension can arise from other conditions:
- Congestive heart failure with pulmonary edema
- Malnutrition or protein‑deficient states
- Abdominal tumors or lymphadenopathy
- Intraabdominal infections or abscesses
Correlate the exam findings with imaging and laboratory data to rule out these alternatives.
Practical Tips for Clinicians
- Always perform the exam in a calm, well-lit environment to reduce patient anxiety.
- Use a consistent order: inspection, palpation, percussion, and auscultation.
- Document findings clearly—note the presence or absence of shifting dullness, fluid wave, and edema.
- When in doubt, schedule an abdominal ultrasound; it can confirm or refute a clinical suspicion in minutes.
Frequently Asked Questions
What is the most reliable bedside test for ascites?
The shifting dullness test, when performed correctly, is highly sensitive for detecting significant fluid volumes in the abdomen.
When should I avoid performing a paracentesis?
Contraindications include coagulopathy (INR >1.5), thrombocytopenia (<50 000 /µL), or localized abdominal wall infection. In such cases, correct the coagulopathy first or use imaging guidance to minimize risk.
Can ascites occur without liver disease?
Yes. Ascites can arise from nephrotic syndrome, congestive heart failure, or malignancies, though portal hypertension remains the most common cause in clinical practice.
How quickly can I expect the fluid to reduce after paracentesis?
Patients often feel immediate relief once a significant volume is removed. However, the abdominal wall may still appear distended until the fluid re‑absorption normalizes over days to weeks, depending on the underlying cause.