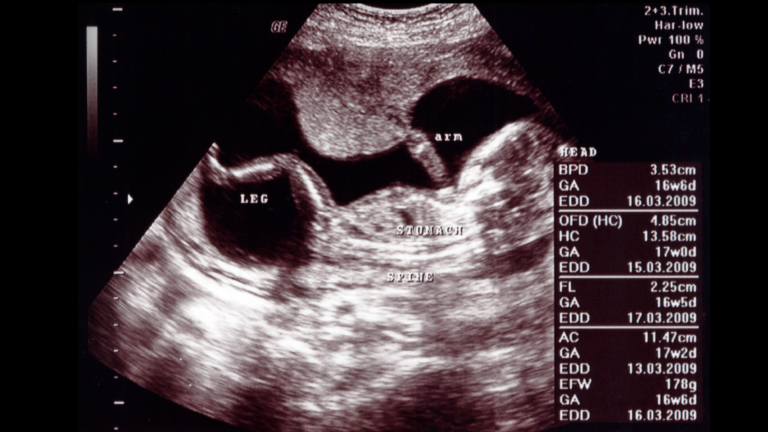
How 37‑Week Fetal Measurements (BPD, HC, AC, FL) Guide Birth Planning
Reaching the 37‑week mark feels like the final stretch before meeting your newborn, and many parents turn to the latest ultrasound to see how big the baby really is. The scan focuses on four key biometry markers—biparietal diameter (BPD), head circumference (HC), abdominal circumference (AC) and femur length (FL). Understanding what these numbers mean can ease anxiety, highlight growth patterns, and sometimes flag issues that need a closer look.
What Each Measurement Tells You
BPD (Biparietal Diameter) measures the width of the skull from one parietal bone to the other. It’s the most reliable single indicator of gestational age because the head grows predictably.
HC (Head Circumference) wraps around the entire skull. While closely linked to BPD, HC captures the overall volume of the brain, helping clinicians assess whether the brain is developing at a normal pace.
AC (Abdominal Circumference) gauges the size of the baby’s abdomen, reflecting liver size and subcutaneous fat. Because AC mirrors nutritional status, it’s a useful barometer for fetal weight estimation.
FL (Femur Length) measures the longest bone in the body. Like BPD, FL follows a fairly steady growth curve and helps confirm the gestational age when paired with the other markers.
Typical Ranges at 37 Weeks
Exact numbers vary by population and equipment, but most obstetric guidelines list the following approximate ranges for a healthy, singleton pregnancy at 37 weeks:
- BPD: 9.5 – 10.5 cm (about 3.7 – 4.1 in)
- HC: 32 – 35 cm (12.6 – 13.8 in)
- AC: 30 – 33 cm (11.8 – 13.0 in)
- FL: 7.5 – 8.5 cm (3.0 – 3.3 in)
If your baby’s measurements fall within these bands, the ultrasound report will usually note “appropriate for gestational age.” Slight deviations—say a BPD a few millimeters larger or smaller—are common and rarely worrisome on their own.
How Doctors Put the Numbers Together
Clinicians don’t look at each value in isolation. Instead, they run the four measurements through established formulas (such as the Hadlock or INTERGROWTH‑21st equations) to estimate fetal weight. The resulting estimated fetal weight (EFW) gives a snapshot of growth trajectory.
When the EFW aligns with the baby’s gestational age, you can feel confident that the pregnancy is progressing normally. A discrepancy of more than 10 %—for instance, an EFW suggesting 34 weeks when the pregnancy is already at 37—might prompt follow‑up scans, extra monitoring, or discussion of potential causes.
Factors That Can Shift the Numbers
Several maternal and fetal variables can nudge the measurements up or down:
- Maternal diabetes: Higher glucose levels often translate to a larger AC because the baby stores extra glycogen and fat.
- Genetics: Parents with larger or smaller builds may naturally pass on those traits, influencing BPD and FL.
- Placental insufficiency: Reduced blood flow can lead to a smaller AC and, occasionally, a reduced HC.
- Multiple gestation: Twins share space and nutrients, sometimes resulting in slightly lower individual measurements.
Because these factors overlap, doctors interpret the data alongside your medical history, blood work, and any symptoms you’ve experienced.
What to Expect During the 37‑Week Scan
The ultrasound technician will first locate the baby’s head, then capture a transverse image to measure BPD and HC. Next, they’ll shift to a cross‑section of the abdomen for AC, and finally slide the probe down to the thigh to gauge FL.
Modern machines produce real‑time images, so you’ll often see the sonographer pause briefly while they place calipers on the exact edges of each structure. The entire process usually takes 15‑20 minutes, and you’ll get a printed report (or digital copy) that lists the four numbers and the corresponding EFW.
When a Measurement Calls for Attention
Most out‑of‑range results are benign, but certain patterns can hint at underlying issues:
- Disproportionately small AC with normal BPD/HC may suggest intrauterine growth restriction (IUGR) due to placental problems.
- Enlarged AC together with elevated maternal glucose could indicate macrosomia, raising the risk of a difficult delivery.
- Significant lag in FL relative to BPD and HC might point to skeletal dysplasia, although this is rare.
If any of these red flags appear, your provider will likely schedule a follow‑up ultrasound in 1‑2 weeks, possibly add Doppler studies of blood flow, and discuss delivery options tailored to the situation.
Preparing for the Scan: Practical Tips
While the ultrasound itself is painless, a few simple steps can make the experience smoother:
- Stay well‑hydrated and have a light snack beforehand; a full bladder isn’t required at 37 weeks, but a comfortable stomach helps.
- Wear loose clothing that allows easy access to your abdomen.
- Bring a list of any recent blood‑test results, especially if you’ve been screened for gestational diabetes.
- Consider jotting down questions—like “How does my baby’s growth compare to the average?”—so you don’t forget them during the appointment.
Putting the Numbers in Perspective
At 37 weeks, you’re technically considered early term, and most babies are ready for life outside the womb. The biometric data simply refines the picture of how ready your baby is. A slightly larger or smaller measurement rarely changes the timing of delivery unless it signals a medical concern.
In most cases, the scan reinforces the reassuring message that your baby is growing on schedule, giving you one more piece of information to celebrate as you approach labor.
Frequently Asked Questions
Is a 37‑week ultrasound mandatory?
No. While many providers schedule it to confirm growth, it’s not a universal requirement. Your obstetrician may skip it if previous scans have shown consistent growth and you have no risk factors.
Can I trust the estimated fetal weight?
EFW is an estimate, not an exact measurement. It’s typically accurate within ±10 % of the baby’s actual weight, which is sufficient for most clinical decisions.
What does it mean if my baby’s BPD is larger than expected?
A larger BPD alone isn’t a problem. It could simply reflect familial head size. Concern arises when BPD is markedly out of range *and* other measurements, like HC or AC, also deviate.
Should I be worried about a small femur length?
Isolated mild reductions in FL are often harmless. However, if FL is significantly shorter than BPD and HC, your doctor might explore possibilities such as skeletal dysplasia or growth restriction.